


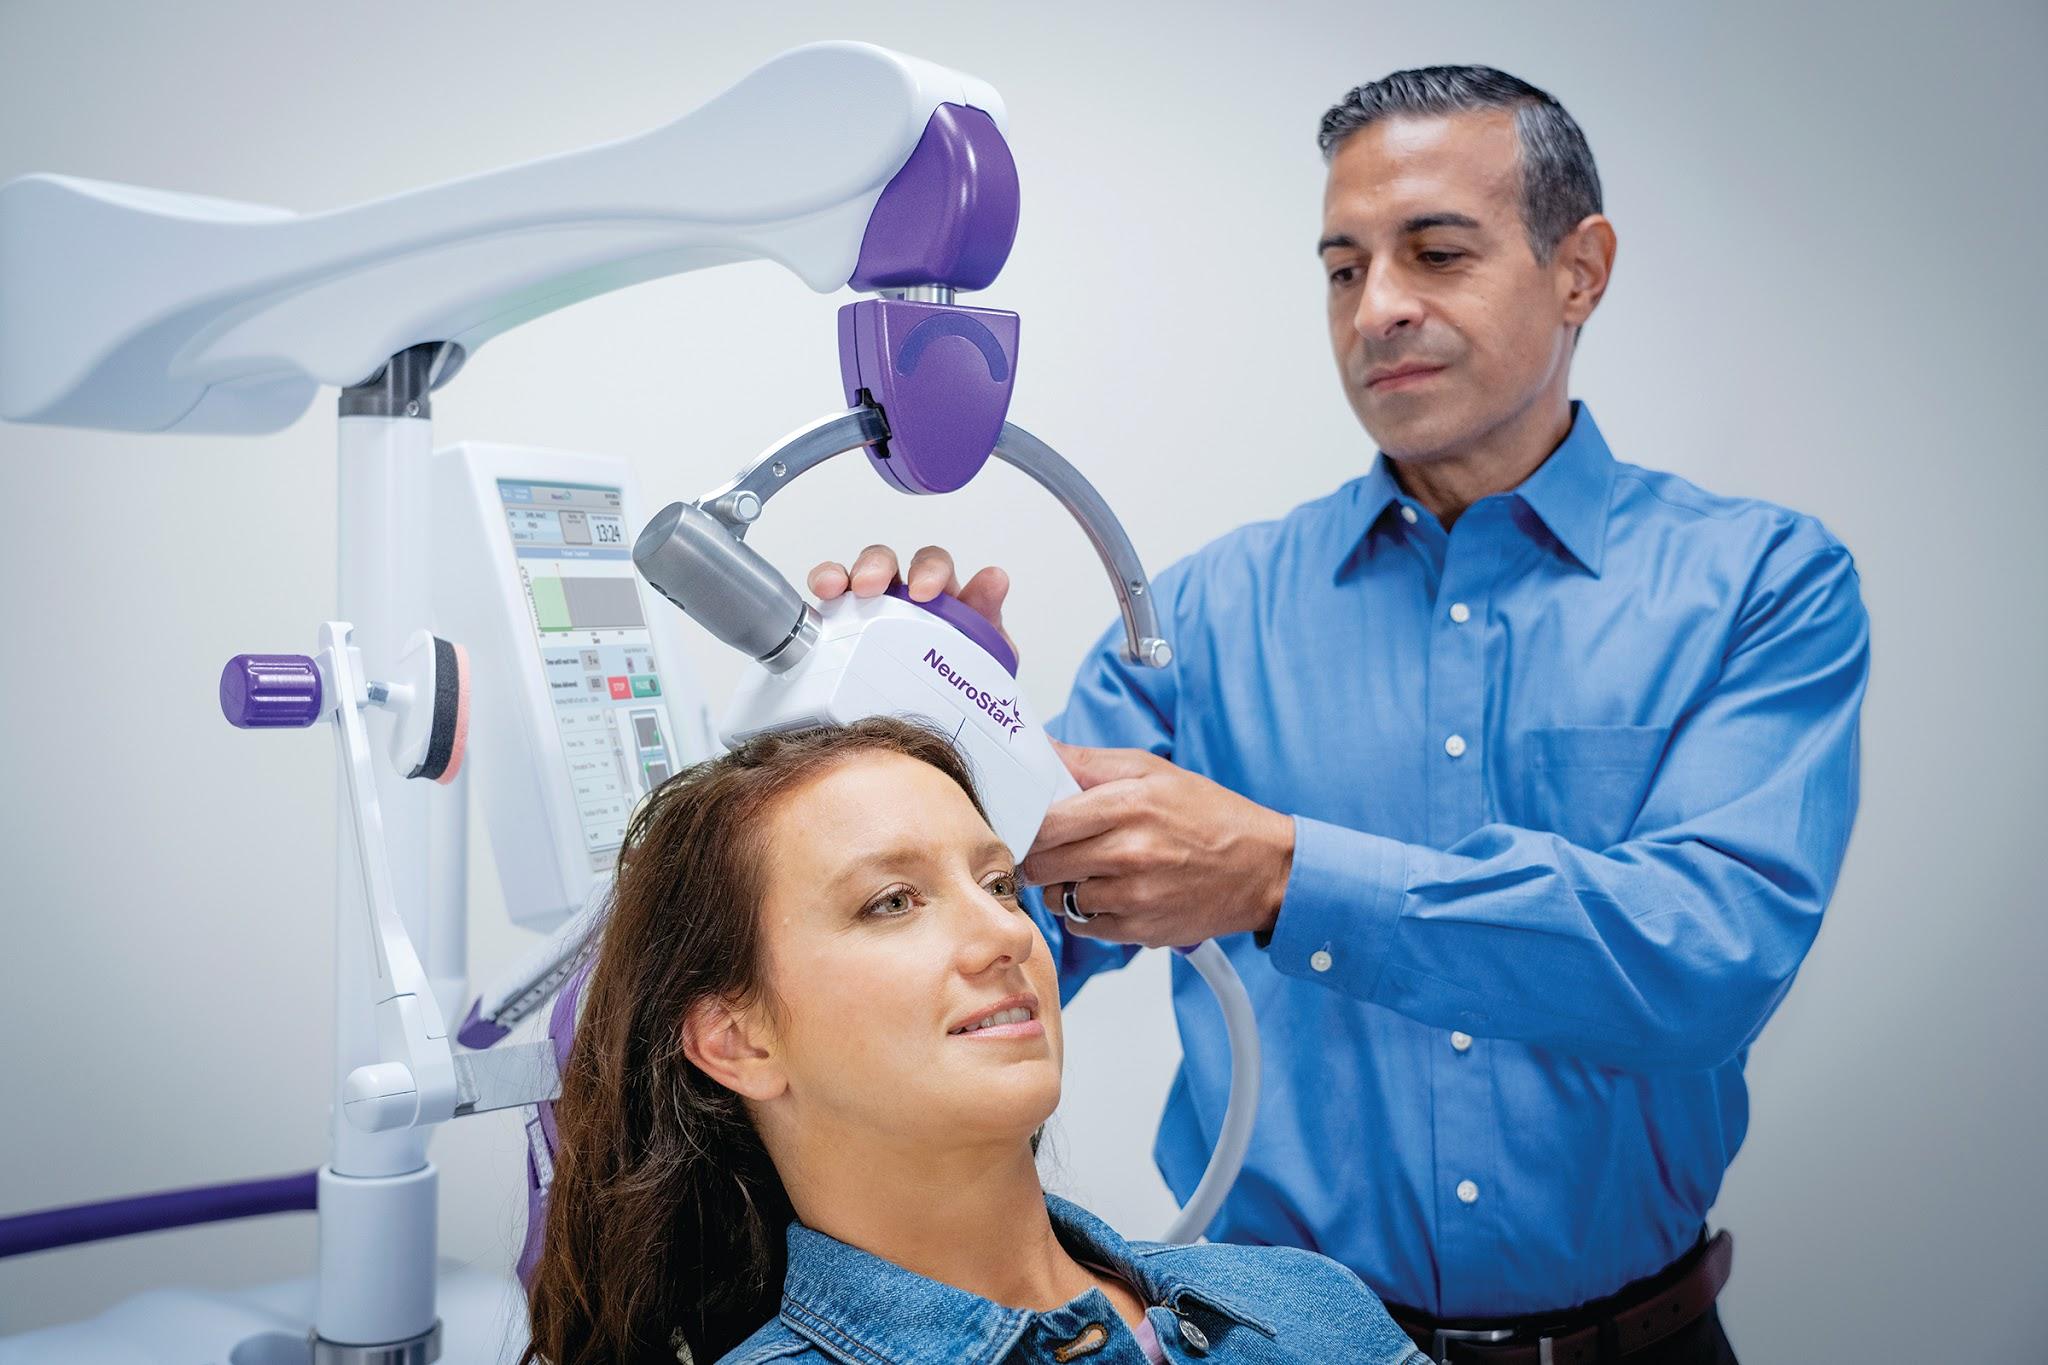
Most TMS therapy side effects involve mild scalp discomfort or a brief headache, avoiding the body-wide complications linked to systemic antidepressants. NeuroStar is an FDA-cleared TMS device for major depressive disorder (ages 15+), as well as OCD and anxious depression in adults.
Most side effects are short-lived. Seizures can happen, but they’re rare. Long-term effects are also worth knowing about before treatment. Keep reading to see what symptoms may show up, what the first week can be like, and what to know about rare and long-term risks.
Key Takeaways
- Scalp discomfort is common: It often improves as treatment continues.
- Most symptoms are brief: Headaches, twitching, or lightheadedness usually fade soon after treatment.
- Serious risks are rare: Seizures are uncommon, but certain risk factors should be discussed with the treatment team.
What Does the First Week of TMS Usually Feel Like?
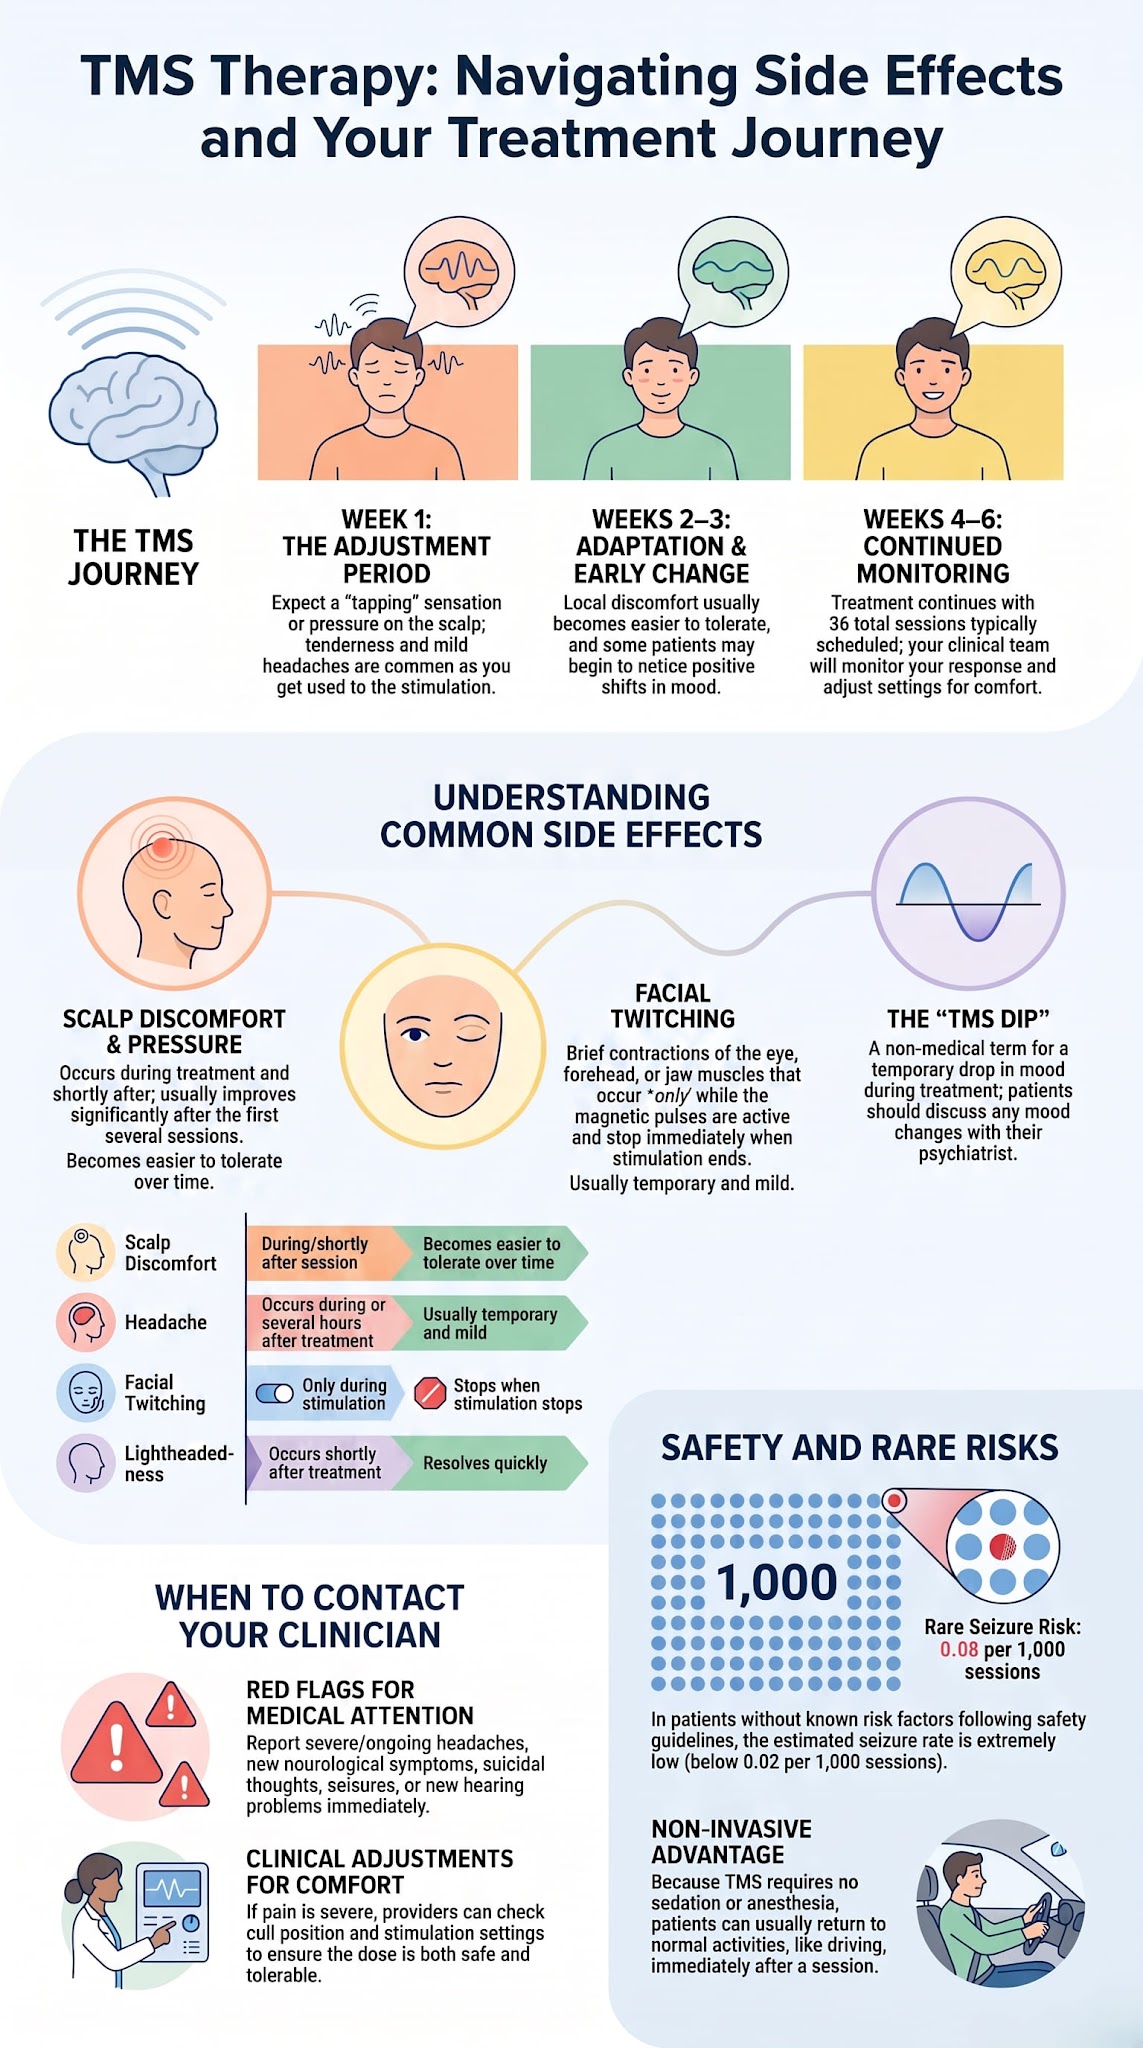
The first week of TMS is often an adjustment period. You may notice tapping or pressure on the scalp, along with some tenderness or a headache during or after treatment. These sensations are usually mild and temporary.
For many patients receiving mental health care in Weston, FL, the discomfort becomes easier to tolerate after the first few sessions. If symptoms are severe, last longer than expected, or keep getting worse, let your treatment provider know. They can check the treatment settings and make adjustments if needed.
Common TMS Therapy Side Effects During Your First Week
NeuroStar reports that discomfort at the treatment site often resolves within the first week. TMS is noninvasive and doesn’t require sedation or anesthesia, so appropriate patients can usually return to their normal activities after each session.
A typical NeuroStar treatment course may include about 36 sessions over six weeks. The schedule can vary based on the treatment plan and the condition being treated.
| Treatment period | Common experience |
| First several sessions | Scalp tapping, pressure, tenderness, or headache |
| End of week 1 | Local discomfort may become easier to tolerate |
| Weeks 2-3 | Some patients begin noticing mood changes |
| Weeks 4-6 | Treatment continues while the response is monitored |
Side effects and symptom improvement don’t always follow the same timeline. Some patients notice changes in depression after about two to three weeks, while others may need more time. A comfortable first week doesn’t guarantee a response, and a difficult first week doesn’t mean TMS won’t help.
The treatment team can also check the coil position and stimulation settings if discomfort is stronger than expected. Proper placement and dosing matter for both comfort and safe treatment.
At Weston Psychological Associates, TMS may be used alongside other psychiatric care, such as medication management, psychotherapy, ADHD treatment, or qEEG neurofeedback when appropriate. This allows the clinical team to look at both symptom changes and treatment tolerance throughout the TMS course.
Can TMS Cause Fatigue, Brain Fog, or the “TMS Dip”?

Some people feel tired, mentally foggy, anxious, or notice changes in sleep or mood during TMS. These symptoms can have more than one cause, so they shouldn’t automatically be blamed on TMS.
“TMS dip” is a term patients often use for a temporary drop in mood during treatment. It isn’t a formal medical diagnosis. If your mood gets worse, talk with your psychiatrist instead of assuming it’s part of the treatment.
TMS is generally well tolerated. Headaches, scalp discomfort, and dizziness are among the more common short-term side effects. Research also suggests that cognitive side effects are uncommon and usually mild or temporary.
Fatigue can be harder to explain. Depression itself can drain your energy. Poor sleep, anxiety, medication changes, and the time needed for regular TMS sessions can also leave you tired. So, your treatment team should look at these factors before deciding that TMS is the cause.
During the first week, some patients may notice scalp tenderness, headaches, facial twitching, or fatigue. These symptoms may become easier to tolerate with continued treatment, but everyone’s response is different.
Worsening depression needs prompt attention. Contact your treatment provider if your mood gets worse, you have suicidal thoughts, or you notice unusual behavior. Don’t assume these changes are a normal part of TMS.
At Weston Psychological Associates, we look at symptoms in the context of your overall care. Comprehensive psychological evaluations, current medication, therapy, sleep habits, anxiety, medical conditions, and your individual response to TMS can all affect how you feel during treatment.
When TMS symptoms need medical attention

Some symptoms should be reported to your TMS treatment team rather than watched at home. Contact your clinician if you have:
- A severe or ongoing headache
- New neurological symptoms
- A major change in mood or anxiety
- Suicidal thoughts or behavior
- A seizure or loss of consciousness
- Severe or ongoing dizziness
- New hearing problems that don’t go away
As highlighted by U.S. Food and Drug Administration
“We recommend that the rTMS device have features that allow: rapid access to the patient; immediate termination of pulsing; rapid removal of the coil from the patient; and the ability to place the patient in a safe position for seizure management.” – U.S. Food and Drug Administration
TMS treatment should be monitored based on each patient’s health and treatment plan. A symptom that seems mild on its own may need more attention if it occurs with a neurological condition, a medication change, or another risk factor.
If you’re unsure whether a symptom is related to TMS, contact your treatment team. It’s safer to discuss a new or unusual symptom than to assume it will pass.
How Long Do TMS Headaches, Scalp Pain, and Twitching Last?
Most TMS headaches and scalp discomfort happen during or soon after a treatment session. Facial twitching is different. It usually occurs only while the magnetic pulses are active.
Research from Clinical Neurophysiol shows
“An update on the possible induction of seizures, theoretically the most serious risk of TMS, is provided. It has become apparent that such a risk is low, even in patients taking drugs acting on the central nervous system, at least with the use of traditional stimulation parameters and focal coils for which large data sets are available.” – Clinical Neurophysiol
| Symptom | Typical duration | Clinical pattern |
| Scalp discomfort | During treatment to shortly afterward | Often becomes easier to tolerate over time |
| Headache | During treatment or for several hours afterward | Usually temporary |
| Facial twitching | During stimulation | Usually stops when stimulation stops |
| Lightheadedness | Shortly after treatment | Usually resolves quickly |
What Should You Expect?

Scalp discomfort may be strongest during the first few treatment sessions. For many patients, it becomes easier to tolerate as treatment continues. Headaches are also usually temporary and may last for several hours after a session.
Facial twitching usually follows a different pattern. The magnetic pulses can cause nearby facial muscles to contract, which may lead to brief twitching around the eye, forehead, or jaw. The movement typically stops when stimulation ends.
If pain is severe, keeps getting worse, or lasts longer than expected, tell your treatment provider. Managing stress through auxiliary support like a relationship wellness intensive program can help lower overall somatic tension, but your clinician should always check the coil position and stimulation settings to decide whether treatment adjustments are needed.
How Rare Is the Seizure Risk With TMS?
Seizures during TMS are rare. One review of more than 318,000 TMS sessions found about 0.08 seizures per 1,000 sessions. In people without known risk factors who were treated within published safety guidelines, the estimated rate was below 0.02 per 1,000 sessions.
The risk isn’t zero. Certain medical conditions, medications, or other factors can lower the seizure threshold. Before treatment, your clinician should review your medical history and current medications. Treatment settings should also follow established safety guidelines.
If you’re considering TMS, talk with your treatment provider about your individual risk. You can also learn more about FDA-cleared NeuroStar TMS Therapy at Weston Psychological Associates. Call or text 988 for 24/7 support if you or someone you know is in crisis.
FAQs
How can TMS scalp discomfort be reduced during treatment?
TMS can cause mild scalp discomfort, especially during the first few sessions. Your clinician may adjust the coil position or lower the stimulation level to make treatment more comfortable. Short breaks may help, too.
If the discomfort is severe, lasts after treatment, or suddenly feels different, tell your clinician.
When should you expect TMS headache relief after treatment?
Mild headaches can happen during or after early TMS sessions. They often become less noticeable as treatment continues. Rest, fluids, and other headache care may help.
Tell your treatment team about headaches that keep coming back, last longer than expected, or interfere with daily activities.
Are Long-Term TMS Therapy Side Effects Possible After Treatment?
Researchers are still studying the long-term effects of TMS. Current evidence shows that TMS has a generally favorable safety record, but each person can respond differently.
If changes in mood, sleep, thinking, or other symptoms continue after treatment, contact your clinician. They can look for other possible causes as well.
What first-week symptoms should you watch for during TMS?
Common early TMS therapy side effects during the first week include scalp tenderness, mild headaches, facial muscle twitching, or lightheadedness. These symptoms often become easier to tolerate with continued treatment.
Watch for symptoms that get worse, don’t go away, or interfere with daily life. Severe or unusual symptoms should be reported to your treatment team.
What should you do if you’re concerned about the rare seizure risk?
Seizures during TMS are rare, but your clinician should review your risk before treatment. Certain health conditions, medications, lack of sleep, and treatment settings can affect seizure risk.
Give your clinician a full medical and medication history. If you have a seizure or unusual neurological symptoms during or after treatment, seek medical care promptly.
References
- https://pubmed.ncbi.nlm.nih.gov/33243615/
- https://www.fda.gov/medical-devices/guidance-documents-medical-devices-and-radiation-emitting-products/repetitive-transcranial-magnetic-stimulation-rtms-systems-class-ii-special-controls-guidance